By Amy Niemas, RN-BC, BSN, MSW, Clinical Content Director · Psychiatric Registered Nurse
Last updated: October 13, 2026
CIWA-Ar Documentation: A Nursing Guide to Alcohol Withdrawal Scoring
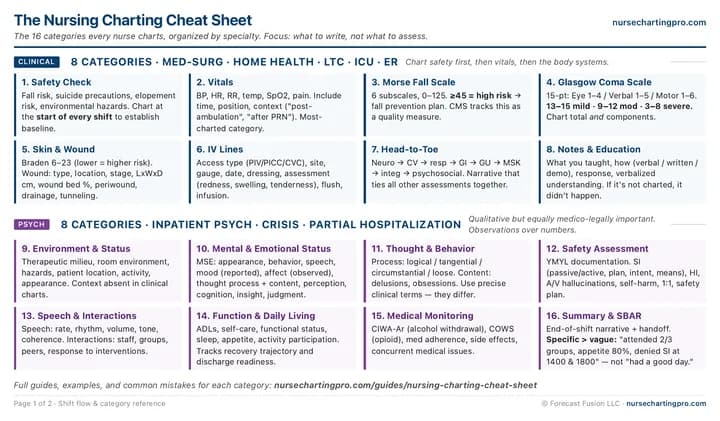
Get the free Nursing Charting Cheat Sheet
- All 16 charting categories, clinical and psych, with what to write for each
- Morse, Braden, Glasgow Coma Scale and SBAR at a glance
- The charting mistakes that cost nurses their licenses
Why This Matters
Regulatory bodies: Centers for Medicare & Medicaid Services (CMS), The Joint Commission, American Society of Addiction Medicine (ASAM)
- Assessment of alcohol withdrawal: the revised CIWA-Ar scale — Sullivan JT et al. Br J Addict. 1989;84(11):1353-1357 (1989)
- Alcohol Withdrawal — Newman RK et al. StatPearls Publishing (Updated 2024) (2024)
- Clinical Practice Guideline on Alcohol Withdrawal Management — American Society of Addiction Medicine (ASAM) (2020)
What CIWA-Ar Measures
How to score each CIWA item
Scoring and Documentation Workflow
The CIWA assessment follows a score-intervene-reassess workflow.
What to Document for Each Assessment
A complete CIWA chart entry has 6 pieces of information.
Protocol Interpretation Basics
Medication Compliance Tracking
Withdrawing patients are commonly on concurrent psychotropics, so medication compliance documentation shows up alongside CIWA scoring in the same shift.
Common Mistakes
Documenting Only the Total Score
Protocols often trigger differently based on elevated items. A total score of 12 driven by tremor and sweats presents a different clinical picture than one driven by agitation and tactile hallucinations. The individual components guide the next action.
Skipping assessments when the patient seems stable
Protocol gaps appear as missed assessments during surveys and legal reviews. "No news" does not qualify as documentation. Even a low score requires documentation at the ordered interval.
Not Documenting the Medication Response
The CIWA protocol follows a loop: assess, medicate, and reassess. Without the post-medication reassessment, you cannot demonstrate that the intervention was effective or justify the next interval.
Vague descriptor language instead of scores
"Appears anxious" is not a CIWA score. Each item has standardized descriptors; use the descriptor and the number. Including the patient's own words in quotes strengthens the documentation.
Using the Wrong Scale for Withdrawal Assessment
CIWA-Ar was developed and validated specifically for alcohol withdrawal. Off-label use for other withdrawal types can lead to misleading scores and inappropriate medication triggers.
Pro Tips
- Remember the 10 CIWA items: Nausea, Tremor, Sweats, Anxiety, Agitation, Tactile, Auditory, Visual, Headache, Orientation. Reviewing this list helps you avoid missing items during a busy shift.
- Document item-level scores every time (i.e. the score for each individual item): Spending an extra minute to document item-level scores pays off when the provider asks, "What specifically was elevated?" A total of 14 holds no clinical significance without knowing which items are driving it.
- Escalate right away if scores are rising quickly: When a CIWA rises from 8 to 15 in one hour, this indicates rapid withdrawal progression - a high mortality scenario. Use your clinical judgment and call the provider as soon as you see this. Also document it, such as: "CIWA rose from 8 to 15 in one hour, provider notified, awaiting orders."
- CIWA and COWS are separate scales - don't mix them: Some patients have both alcohol and opioid use disorder and may need both assessments. Document each scale separately, using its full name (CIWA-Ar, COWS), and never combine the scores.
Step by Step
- Assess each item using standardized descriptors: Evaluate all 10 CIWA items with the standardized descriptors on the scoring sheet. Assess the patient by asking about each symptom and observing for objective signs.
- Calculate the total score: Sum all item scores. Compare the total to your facility's protocol thresholds to determine the required intervention.
- Administer medication per protocol: If the score triggers a medication order, administer as-needed (PRN) medication and document the time, dose, and route of administration.
- Document the complete assessment: Document the time, all item-level scores, total, protocol action taken, and time of the next scheduled assessment.
- Reassess after intervention: If medication was given, reassess within 30-60 minutes per protocol. Document the post-medication score and the patient's response.
Frequently Asked Questions
- What does CIWA stand for?
- CIWA stands for Clinical Institute Withdrawal Assessment. The revised version, CIWA-Ar, serves as the standard 10-item scale for assessing alcohol withdrawal severity. Researchers developed it in 1989 at the Addiction Research Foundation in Toronto.
- What is the difference between CIWA and COWS?
- CIWA-Ar assesses alcohol withdrawal (10 items, total 0-67), while COWS (the Clinical Opiate Withdrawal Scale) assesses opioid withdrawal (11 items, total 0-48). They measure different withdrawal syndromes and should never be used interchangeably.
- What CIWA score requires medication?
- Most protocols trigger as-needed (PRN) benzodiazepines at a CIWA-Ar score of 10 or above, but thresholds vary by facility. Always follow your facility's specific protocol instead of generic guidelines.
- How often should CIWA be scored?
- How often you score CIWA depends on the score and your facility's protocol. Common intervals: every 1 hour if the score is above 8, every 2 hours if stable in the 5-8 range, every 4 hours if stable and below 5, and every 8 hours if stable after the initial assessment period. After administering as-needed (PRN) medication, reassess within 30-60 minutes.
Get the free Nursing Charting Cheat Sheet
- All 16 charting categories, clinical and psych, with what to write for each
- Morse, Braden, Glasgow Coma Scale and SBAR at a glance
- The charting mistakes that cost nurses their licenses
Chart faster with Nurse Charting Pro
Tap through your assessments during the shift and get a draft of your note to review at clock-out. Your notes are cleared from your phone at the end of your shift.
Related Guides
- COWS DocumentationThe opioid-withdrawal counterpart. Same score-intervene-reassess loop, different scale, different protocol triggers.
- Glasgow Coma Scale ChartingNeurological monitoring plays a core role in withdrawal assessment. GCS trends paired with CIWA can catch decompensation early.
- SBAR Nursing HandoffCIWA trends play a key role in any SBAR for a withdrawing patient.
- Nursing Charting Cheat SheetAll charting categories in one scannable reference.
- RASS documentation for ICU sedationThe RASS, used primarily in the ICU setting, is the closest documentation method to the CIWA. Both follow the same score-intervene-reassess loop; charting habits transfer directly.
- Psychiatric Nursing Charting overviewWithdrawal monitoring is common on both psychiatric and medical units. CIWA bridges clinical and psychiatric documentation.