CIWA-Ar Documentation: A Nursing Guide to Alcohol Withdrawal Scoring
How to score and document the CIWA-Ar alcohol withdrawal assessment. 10 items, scoring examples, and protocol-triggered interventions for nurses.
On this page 13 sections
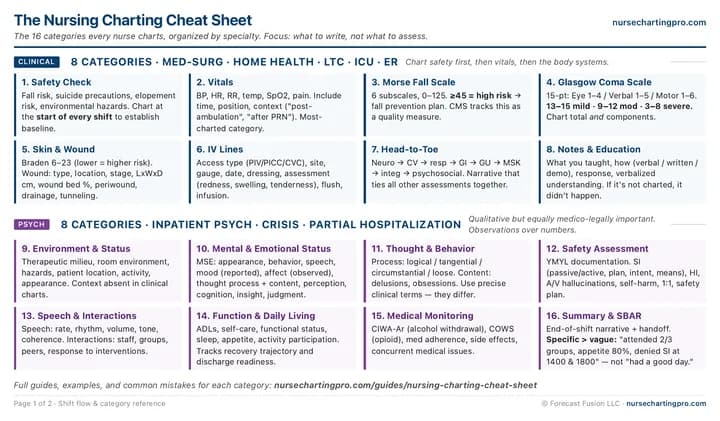
Get the free Nursing Charting Cheat Sheet
- All 16 charting categories, clinical and psych, with what to write for each
- Morse, Braden, Glasgow Coma Scale and SBAR at a glance
- The charting mistakes that cost nurses their licenses
Why this matters
- Centers for Medicare & Medicaid Services (CMS)
- The Joint Commission
- American Society of Addiction Medicine (ASAM)
Unrecognized or undertreated alcohol withdrawal carries approximately 5% mortality. The CIWA serves as a safety tool rather than merely a paperwork exercise. Protocol-driven medication, such as lorazepam PRN for CIWA ≥10, means the score directly triggers a clinical action; an incorrect score results in an inappropriate action. Gaps in CIWA documentation during active withdrawal are frequently tagged in surveys and expose the nurse and facility to malpractice claims, regulatory citations, and licensing board complaints if the chart is later reviewed.
- Assessment of alcohol withdrawal: the revised CIWA-Ar scale Sullivan JT et al. Br J Addict. 1989;84(11):1353-1357, 1989
- Alcohol Withdrawal Newman RK et al. StatPearls Publishing (Updated 2024), 2024
- Clinical Practice Guideline on Alcohol Withdrawal Management American Society of Addiction Medicine (ASAM), 2020
What CIWA-Ar Measures
The CIWA-Ar (Clinical Institute Withdrawal Assessment for Alcohol, revised) is a 10-item scale that assesses the severity of alcohol withdrawal. Each item scores between 0 and 7, except for orientation, which scores between 0 and 4. The total range is 0-67, although scores above 45 are rare in practice. Sullivan, Sykora, Schneiderman, Naranjo, and Sellers developed the CIWA-Ar at the Addiction Research Foundation in Toronto, publishing it in 1989. This scale replaced the original CIWA, which lacked rigorous validation. It is used in detox units, medical and psychiatric floors, emergency departments, and ICUs - anywhere a patient may experience alcohol withdrawal. The 10 items include: nausea and vomiting (0-7), tremor (0-7), paroxysmal sweats (0-7), anxiety (0-7), agitation (0-7), tactile disturbances (0-7), auditory disturbances (0-7), visual disturbances (0-7), headache/fullness in head (0-7), and orientation/clouding of sensorium (0-4).
How to score each CIWA item
Most CIWA items use a 0-7 descriptive scale where 0 means the symptom is not present and 7 means the symptom is at its most severe. Use the standardized descriptors on the scoring sheet, not your own interpretation. The following are examples of these descriptions, but it is not a comprehensive list. For tremor: 0 = no tremor, 1 = not visible but can be felt fingertip to fingertip, 4 = moderate with arms extended, 7 = severe even with arms not extended. For anxiety: 0 = no anxiety, 1 = mildly anxious, 4 = moderately anxious/guarded, 7 = equivalent to acute panic states. For tactile disturbances: 0 = none, 1 = very mild itching/pins and needles/burning/numbness, 4 = moderate hallucinations, 7 = continuous hallucinations. Scoring is subjective for many items - consistency across assessors is a known challenge. The best defense is to: document WHAT you observed alongside the score. "Tremor 4 (moderate, visible with arms extended)" is more defensible than "Tremor 4" alone.
Scoring and Documentation Workflow
The CIWA assessment follows a score-intervene-reassess workflow.
Step 1: Assess at the ordered interval. Step 2: Score each item per the standardized descriptors. Step 3: Sum the total. Step 4: Compare the total to your facility's protocol thresholds. Step 5: Administer medication if the protocol indicates and you have an active order. Step 6: Document everything - time, item scores, total, action taken, and reassessment plan. Step 7: Schedule the next assessment per the protocol. This is a loop, not a one-time event. After medication administration, reassess within 30-60 minutes (per protocol) to document the response. The reassessment is part of the loop - do not skip it.
What to Document for Each Assessment
A complete CIWA chart entry has 6 pieces of information.
1. Time of assessment (military time - CIWA is time-sensitive and protocols are interval-based). 2. Item-level scores (detailing the number value for each item, not just the total score). 3. Total score. 4. Protocol action taken (medication given, none needed, or escalated to provider). 5. Patient response (if medication was given and you have reassessed). 6. Time of next scheduled assessment. Example format: 1400 CIWA-Ar 12 (Nausea 2, Tremor 4, Sweats 3, Anxiety 2, Agit 1, Tactile 0, Auditory 0, Visual 0, Headache 0, Orient 0). Per protocol: lorazepam 2mg PO given at 1405. Next assessment 1500.
Protocol Interpretation Basics
CIWA protocols vary by institution - always use YOUR facility's protocol, not a generic one from the internet. That said, most follow a common pattern. A typical CIWA protocol might be: score <10 - no medication, monitor per schedule. Score 10-18 - PRN benzodiazepine (usually lorazepam 1-2mg or diazepam 5-10mg). Some facilities use phenobarbital. Follow your facility's guidelines. Score ≥19 - PRN medication plus provider notification. Some protocols may have fixed-schedule dosing above this threshold, or may have fixed-dose scheduling from the start. Know your protocol's re-score intervals: commonly Q1h if the score is elevated, Q2h if stable mid-range, Q4h if stable, and Q8h if stable and low.
Medication Compliance Tracking
Withdrawing patients are commonly on concurrent psychotropics, so medication compliance documentation shows up alongside CIWA scoring in the same shift.
The framework (compliant, partial, refusing) and the refusal → education → outcome documentation loop are covered in the Psychiatric Nursing Charting guide. Use the same pattern for any psychotropic given during the withdrawal protocol.
Common mistakes
Documenting Only the Total Score
Protocols often trigger differently based on elevated items. A total score of 12 driven by tremor and sweats presents a different clinical picture than one driven by agitation and tactile hallucinations. The individual components guide the next action.
Skipping assessments when the patient seems stable
Protocol gaps appear as missed assessments during surveys and legal reviews. "No news" does not qualify as documentation. Even a low score requires documentation at the ordered interval.
Not Documenting the Medication Response
The CIWA protocol follows a loop: assess, medicate, and reassess. Without the post-medication reassessment, you cannot demonstrate that the intervention was effective or justify the next interval.
Vague descriptor language instead of scores
"Appears anxious" is not a CIWA score. Each item has standardized descriptors; use the descriptor and the number. Including the patient's own words in quotes strengthens the documentation.
Using the Wrong Scale for Withdrawal Assessment
CIWA-Ar was developed and validated specifically for alcohol withdrawal. Off-label use for other withdrawal types can lead to misleading scores and inappropriate medication triggers.
Pro tips
- Remember the 10 CIWA itemsNausea, Tremor, Sweats, Anxiety, Agitation, Tactile, Auditory, Visual, Headache, Orientation. Reviewing this list helps you avoid missing items during a busy shift.
- Document item-level scores every time (i.e. the score for each individual item)Spending an extra minute to document item-level scores pays off when the provider asks, "What specifically was elevated?" A total of 14 holds no clinical significance without knowing which items are driving it.
- Escalate right away if scores are rising quicklyWhen a CIWA rises from 8 to 15 in one hour, this indicates rapid withdrawal progression - a high mortality scenario. Use your clinical judgment and call the provider as soon as you see this. Also document it, such as: "CIWA rose from 8 to 15 in one hour, provider notified, awaiting orders."
- CIWA and COWS are separate scales - don't mix themSome patients have both alcohol and opioid use disorder and may need both assessments. Document each scale separately, using its full name (CIWA-Ar, COWS), and never combine the scores.
Step by step
- Assess each item using standardized descriptorsEvaluate all 10 CIWA items with the standardized descriptors on the scoring sheet. Assess the patient by asking about each symptom and observing for objective signs.
- Calculate the total scoreSum all item scores. Compare the total to your facility's protocol thresholds to determine the required intervention.
- Administer medication per protocolIf the score triggers a medication order, administer as-needed (PRN) medication and document the time, dose, and route of administration.
- Document the complete assessmentDocument the time, all item-level scores, total, protocol action taken, and time of the next scheduled assessment.
- Reassess after interventionIf medication was given, reassess within 30-60 minutes per protocol. Document the post-medication score and the patient's response.
Frequently asked questions
What does CIWA stand for?
What is the difference between CIWA and COWS?
What CIWA score requires medication?
How often should CIWA be scored?
Get the free Nursing Charting Cheat Sheet
- All 16 charting categories, clinical and psych, with what to write for each
- Morse, Braden, Glasgow Coma Scale and SBAR at a glance
- The charting mistakes that cost nurses their licenses
Chart faster with Nurse Charting Pro
Tap through your assessments during the shift and get a draft of your note to review at clock-out. Your notes are cleared from your phone at the end of your shift.


Related guides
- psychCOWS DocumentationThe opioid-withdrawal counterpart. Same score-intervene-reassess loop, different scale, different protocol triggers.
- clinicalGlasgow Coma ScaleNeurological monitoring plays a core role in withdrawal assessment. GCS trends paired with CIWA can catch decompensation early.
- SBAR Nursing HandoffCIWA trends play a key role in any SBAR for a withdrawing patient.
- Nursing Charting Cheat SheetAll charting categories in one scannable reference.
- clinicalRASS DocumentationThe RASS, used primarily in the ICU setting, is the closest documentation method to the CIWA. Both follow the same score-intervene-reassess loop; charting habits transfer directly.
- psychPsychiatric Nursing ChartingWithdrawal monitoring is common on both psychiatric and medical units. CIWA bridges clinical and psychiatric documentation.